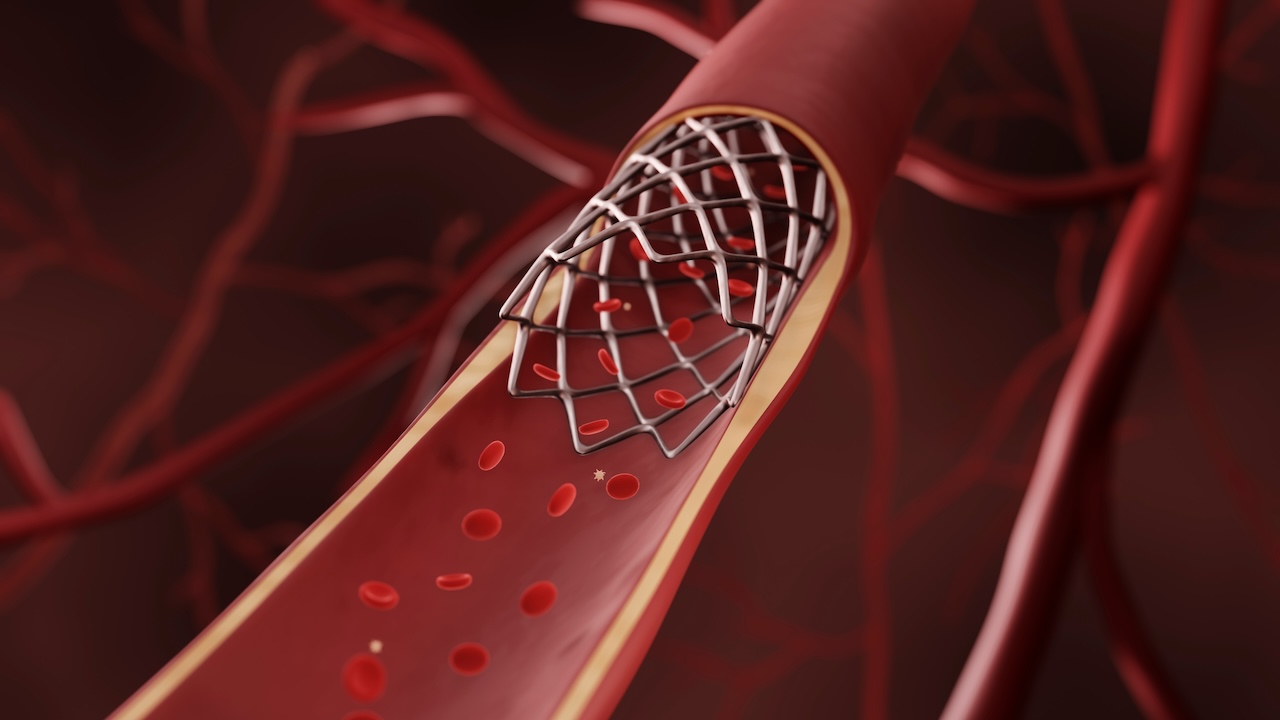

A new chip replicates the blood vessels of individual patients. The ‘vessel-on-a-chip’ enables personalised predictions of stroke risk, rather than the population-wide averages that doctors currently rely on. The project, called ‘Physical Twin’, is on this year’s shortlist for the Eureka Prizes and is one of eleven research projects from the university that have been nominated for these awards.
The Eureka Prizes are one of the most prestigious awards for science and innovation in Australia. The development is the work of Professor Arnold Ju’s team. The team combines chip technology with 3D printing and generative artificial intelligence (AI). Using the chip, the researchers aim to determine why clots in some patients actually break loose and travel through the bloodstream to cause a stroke, a question to which existing risk models do not provide a satisfactory answer.
Factors that vary from patient to patient
The research was prompted by a clinical problem. The risk of an ischaemic stroke, in which a blockage cuts off the blood supply to the brain, is difficult to predict in practice. For example, the process whereby a blood clot breaks loose and becomes lodged elsewhere depends heavily on factors that vary from patient to patient.
Various existing models are available, such as simple flow chambers with a flat, uniform vessel shape, or animal models that do not accurately mimic human clotting processes. However, according to the researchers, these do not take sufficient account of these individual differences. Previous chip technologies also often used generic designs rather than the vascular anatomy of a specific patient, or cell types that are not suited to a carotid artery.
From average risk profiles to individual assessment
Cardiovascular diagnostics have traditionally relied on average risk profiles, which are derived from large patient populations and are not tailored to individual patients. The team aims to change this. The approach makes it possible to replicate an individual patient’s vascular structure and blood flow on a chip. This creates a physical miniature replica of the blood vessel, which behaves identically to the original. This provides doctors with a tool to identify risk factors that would otherwise go unnoticed with an approach based on averages.
The team reconstructed the carotid arteries of six patients using clinical scans. The patients’ vascular geometry was then converted into a microfluidic design and fabricated on glass using a high-resolution 3D printing technique, thereby preserving the bends, narrowings and local curvature of the original blood vessel. The channels are lined with human type I collagen. They are also coated with a layer of human endothelial cells from the carotid artery. These cells were cultured under flow conditions and have thus developed into arterial tissue that resembles the inside of a real blood vessel.
Among other things, the researchers discovered that a pulsating blood flow, such as that created in the body by the heartbeat, inhibits clot formation and reduces the detachment of fragments. This effect is independent of the average flow rate. A constant flow, on the other hand, appears to lead to detachment more frequently.
Von Willebrand factor
A protein called von Willebrand factor (VWF) plays a crucial role in this process. This protein changes shape under the influence of mechanical forces. Under calm conditions, it remains folded, but when sufficient flow force is applied, it unfolds and can bind to platelets. In patients with strong, concentrated blood flow, this unfolding mechanism appears to be the main driver of clot formation. In these patients, agents that block this mechanism significantly inhibited both the growth of the clot and the release of fragments.
In patients with slower, disrupted blood flow, the same treatments were actually much less effective at reducing the size of the clot. The researchers point out that one substance, an antibody called 6G1, actually increases the likelihood of fragments breaking off in this group without reducing the size of the clot. Another component of the same protein system – the binding between VWF and a platelet receptor called integrin αIIbβ₃ – appears to be essential in these patients for maintaining the mechanical stability of the clot. When this binding was blocked during the study, the clot remained the same size. However, it fragmented much more frequently, which the researchers describe as a ‘brittle clot’.
Simplified model
Using a simplified model comprising just a single blood vessel branch – with the same flow velocity at the site of injury but without the branching – the researchers demonstrated that these differences are due to the shape of the vessel and not solely to the local flow velocity. In this simplified model, significantly fewer fragments were dislodged than in the complete, branched model. This demonstrates that, in addition to flow velocity, the three-dimensional shape of the blood vessel – including bends and localised turbulence in the blood flow – also plays a role in the risk of fragment dislodgement.
The team also compared the number of detachments measured on the chip with the severity of the stroke actually suffered by the patient in question. Patients in whom many fragments detached on the chip were found to have more frequently suffered a stroke affecting a larger area of the brain. Based on this, the research team proposes a preliminary model in which the patient-specific chip first classifies a patient’s blood flow type. This insight can then be used to determine the appropriate blood-thinning medication and corresponding dosage, or to better assess the need for intervention in individual patients. The researchers emphasise that, given the small patient group of just six people, this should be regarded as a proof of concept.